A Practical Guide to Infection Escalation
A small change in a wound, urine colour, stoma output or blood glucose reading can become a serious clinical concern far more quickly than families and support teams expect. This guide to infection escalation is designed for NDIS participants with complex health needs, and for the people responsible for noticing changes early, acting safely and documenting what happened.
Infection does not always begin with a dramatic symptom. For a person with reduced sensation, communication differences, diabetes, a catheter, stoma, pressure area or chronic wound, the first sign may be subtle: unusual tiredness, increased pain, new confusion, reduced appetite or a change in usual behaviour. Safe escalation depends on knowing the participant’s baseline, recognising what is different, and involving the right health professional without delay.
What infection escalation means in clinical support
Infection escalation is the structured process of moving a concern from observation to clinical review, urgent medical assessment or emergency care according to the seriousness of the signs. It is not simply reporting that a participant looks unwell. It requires clear observations, timely action, good communication and an accurate record.
For support workers and families, this means following the participant’s clinical care plan and reporting changes promptly. For Support Coordinators and providers, it means ensuring there is a workable pathway for concerns after hours, during staff changes and when a participant’s presentation deteriorates. For nurses, it means assessing risk, advising on immediate safe care within scope, liaising with treating teams where appropriate, and updating care instructions after review.
The aim is to help participants stay safe at home while avoiding both underreaction and unnecessary panic. The correct response depends on the person, their known health conditions, the likely source of infection and how quickly symptoms are changing.
Recognise changes before they become an emergency
A reliable escalation process starts well before there is a suspected infection. Teams need practical nursing assessments that establish what is normal for the participant: their usual alertness, skin appearance, wound drainage, continence pattern, catheter output, stoma routine, temperature range if monitored, diabetes management plan and communication cues.
Without a baseline, it is easy to dismiss a significant change as a usual fluctuation, or to escalate a longstanding issue without useful clinical detail. A nurse-led care plan should state what staff are expected to observe, what they can do, who they must contact and which symptoms require urgent action.
Common infection warning signs
The source of an infection may be a wound, pressure injury, urinary tract, catheter site, stoma site, chest, bowel or skin fold. Signs can vary, but staff should take the following changes seriously:
- fever, chills, sweating, or feeling unusually hot or cold
- increasing redness, swelling, heat, pain, odour or discharge from a wound, skin area, stoma site or catheter site
- cloudy, foul-smelling or bloody urine, pain or discomfort, blocked catheter drainage, or a marked change in urine output
- new confusion, drowsiness, agitation, weakness, reduced food or fluid intake, vomiting, or a sudden decline in usual function
- fast breathing, shortness of breath, chest pain, blue or grey lips, fainting, or a participant who is difficult to rouse
Not every change means an infection is present. A wound may have increased moisture from dressing failure, and concentrated urine may follow reduced fluid intake. However, uncertainty is a reason to seek clinical advice, particularly where a participant has diabetes, immune suppression, poor circulation, a history of recurrent infections or limited ability to report pain.
A guide to infection escalation: what to do first
When a concern is identified, staff should remain calm and work through the existing clinical care plan. Start by checking immediate safety. Is the participant conscious, breathing comfortably and responding as usual? Is there a rapid deterioration, severe pain, uncontrolled bleeding, seizure activity, chest pain or signs that could indicate sepsis?
If the participant is severely unwell or their condition is rapidly worsening, call 000 for emergency assistance. Do not wait for a routine nursing visit, a family callback or the next rostered shift. Staff should stay with the participant where safe to do so, provide first aid or care within their training and plan, and share clear information with ambulance clinicians.
If the concern is urgent but not immediately life-threatening, contact the treating GP, relevant specialist service, after-hours medical service or the participant’s nominated clinical contact according to the care plan. A registered nurse can help assess the urgency and guide the escalation pathway, but nursing input should never delay emergency medical care.
Avoid trying to solve a possible infection with unapproved remedies, leftover antibiotics or changes to prescribed medication. Antibiotics need medical assessment and prescribing. Catheters, stomas, wounds and diabetes routines also have specific risks, so staff should only perform tasks they are trained and authorised to complete.
Give clinicians useful information
A vague message such as the participant seems off does not give a GP, nurse or emergency clinician enough to act confidently. Clear reporting protects the participant and helps prevent repeated calls for missing information.
Record when the change was first noticed, what was observed, how it compares with the participant’s usual presentation, and whether symptoms are worsening. Include relevant observations available under the care plan, such as temperature, blood glucose result, fluid intake, urine output, bowel pattern, wound appearance or oxygen saturation where trained staff have approved equipment and instructions.
Also document what action was taken, who was contacted, the time of contact, advice received and whether the participant, guardian or family member was informed. If a participant has communication needs, note how pain, discomfort and consent were assessed. This is not paperwork for its own sake. It creates a safe handover between support workers, nurses, medical teams and families.
Escalation for wounds, pressure areas and skin changes
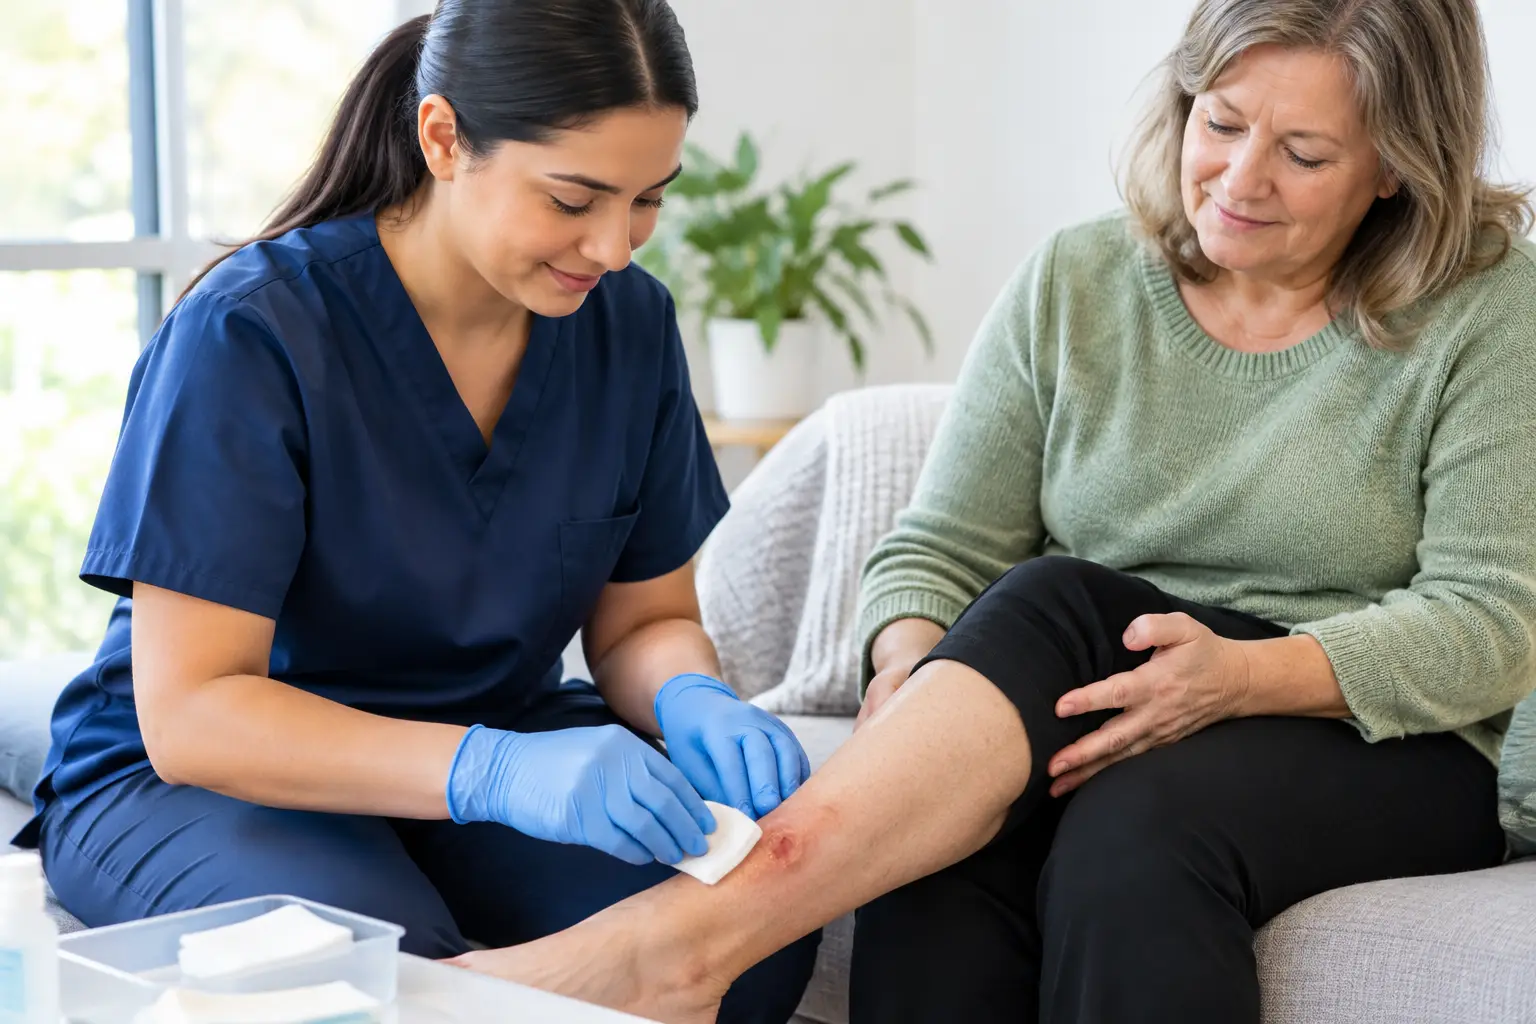
Pressure injuries and chronic wounds can deteriorate quickly when infection develops. Redness spreading beyond the wound edge, increased heat, swelling, escalating pain, purulent discharge, offensive odour, unexpected bleeding or tissue colour changes all require prompt clinical review.
People with reduced mobility, diabetes, poor nutrition, vascular disease or reduced sensation may not experience or report pain in the expected way. A new refusal to transfer, sleep disturbance, increased distress during personal routines or withdrawal from usual activities may be an early clue that a pressure area is worsening.
A nurse-led assessment can determine whether the current dressing regime, pressure care approach and monitoring frequency remain appropriate. It can also identify when the issue needs GP review, wound clinic involvement or urgent hospital assessment. Importantly, staff should not photograph wounds or share images unless this is authorised by the participant’s plan, privacy processes and clinical direction.
Urinary, catheter and stoma concerns need a specific response
Catheter-related infections and blockages are common escalation points because symptoms can overlap. A blocked catheter, leaking bypass, lower abdominal discomfort, new agitation, fever, reduced drainage or blood in the urine requires timely action under the participant’s catheter care plan. If there is no urine draining and the participant is in pain or becoming unwell, this should be treated as urgent.
For participants with a stoma, changes such as increasing redness around the site, painful skin breakdown, unusual discharge, fever, a major change in output, persistent vomiting or a stoma that looks dark, pale or unusually swollen require escalation. Some changes in output can relate to food, fluids or medication, but a sudden change combined with pain or systemic illness should not be managed as a routine support issue.
Practical nursing assessments are particularly valuable for recurrent catheter or stoma concerns. They can clarify the likely trigger, check whether staff are following the correct routine, and provide support worker training and clinical oversight to reduce avoidable complications.
Why training and care plans matter after an incident
Once the immediate issue has been addressed, the work is not finished. Repeated infections, delayed identification or inconsistent responses are signs that the clinical care plan may need review. This could include clearer observation instructions, a revised escalation flow, updated wound or continence routines, defined after-hours contacts, or more targeted staff training.
Support workers need more than a list of tasks. They need to understand the reason for key observations, the difference between routine variation and a red flag, and the limits of their role. Training should be practical and specific to the participant’s catheter, stoma, wound, pressure care needs, diabetes plan or bowel and bladder routine.
For Support Coordinators, a nursing report can provide clear evidence of clinical risk, current care requirements, staff competency needs and recommendations for ongoing complex health support. Clear reports for Support Coordinators are particularly useful when care needs have changed and additional clinical oversight or revised supports must be considered.
When to seek nurse-led NDIS care
Referral for nurse-led NDIS care is appropriate when a participant has recurring infections, complex wounds, pressure injury risk, catheter or stoma complications, poorly defined escalation instructions, or a support team that needs clinical training. It is also appropriate after a hospital presentation where discharge information needs translating into safe, workable care at home.
Compassion Wings provides clinical support in the home across Adelaide, including practical nursing assessments, clinical care plans, wound and pressure care, continence and catheter support, and training for the workers implementing care. The focus is safe, dignity-focused care that gives families reassurance and gives referrers a clear clinical pathway.
The best escalation plan is the one a support worker can follow at 2 am, a family member can understand under pressure, and a clinician can rely on when making decisions. Put that plan in place before the next small change has the chance to become a serious one.