How to Prepare Nursing Referrals That Get Action
A referral that says “needs nursing support” can delay care when a participant has a leaking catheter, recurring wounds or support workers unsure how to follow a diabetes routine. The quickest path to appropriate clinical support is a referral that explains what is happening now, what has already been tried and what risk needs to be assessed.
Knowing how to prepare nursing referrals well helps Support Coordinators, families, discharge teams and SIL providers obtain practical nursing assessments sooner. It also gives the receiving nurse enough information to prioritise risk, plan the first visit and produce evidence that is useful for NDIS reviews or a change of circumstances.
Start with the clinical reason for referral
Be specific about the problem requiring nurse-led NDIS care. “Continence issues” is a broad description. A clearer referral may explain that the participant has frequent urinary leakage, skin redness, increased pad use, recurrent urinary tract infections or a current catheter that support workers are not confident managing.
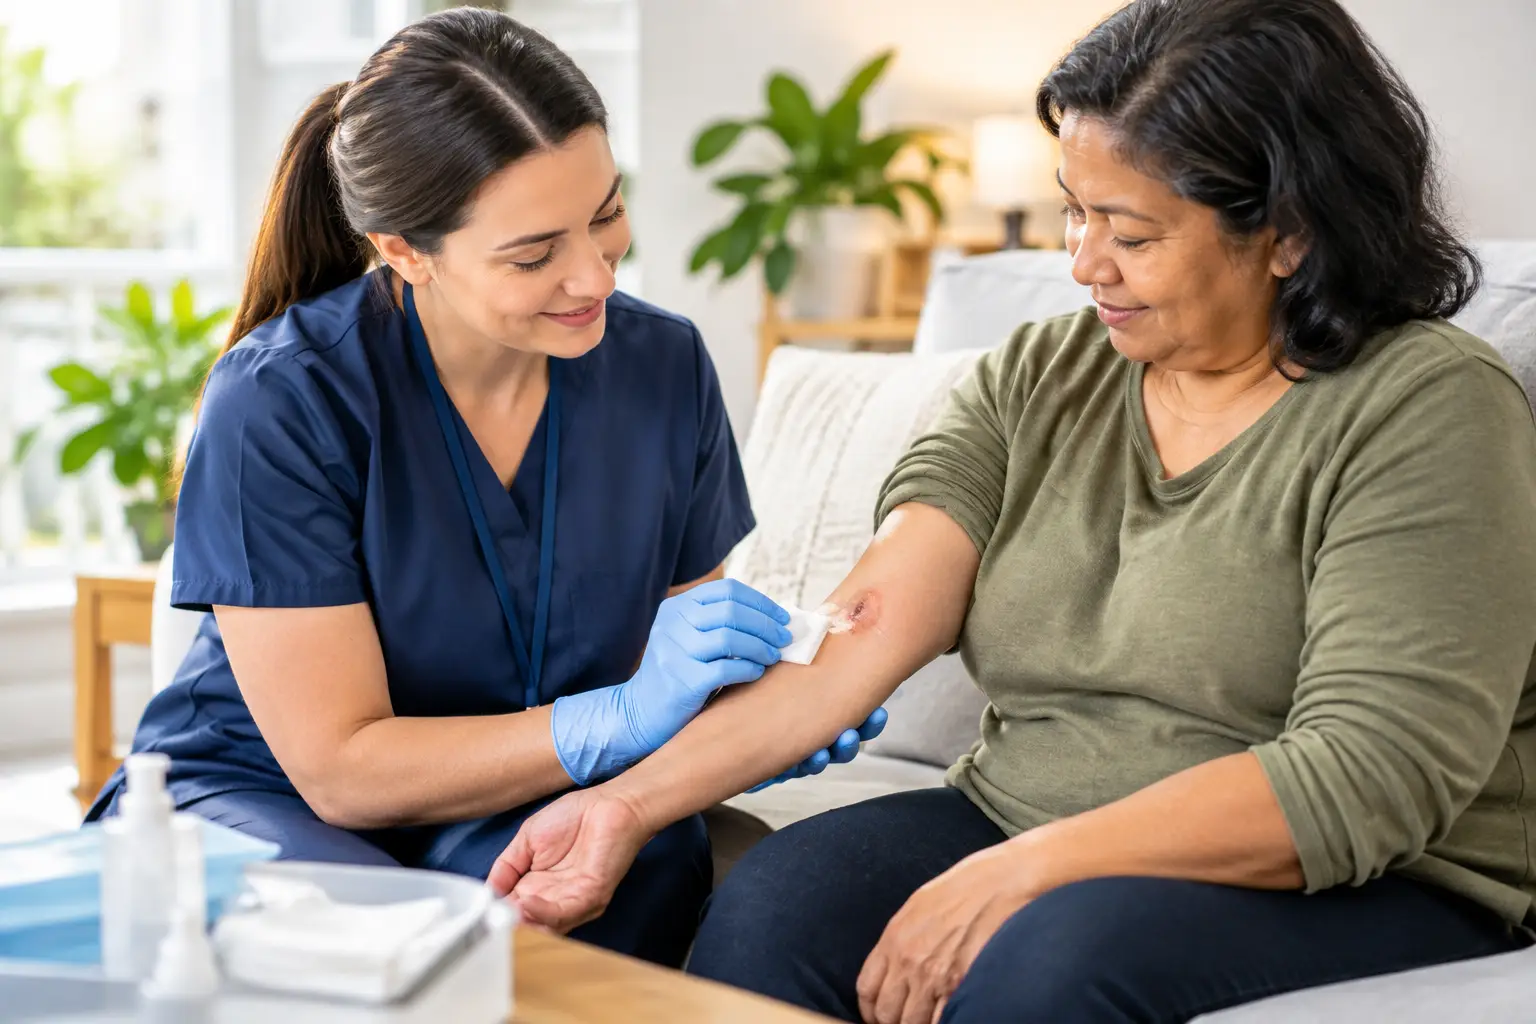
The same principle applies to wound care, stoma support, bowel routines, pressure care, medication oversight and diabetes management. Describe the current issue, its effect on the participant’s daily care and the nursing question that needs answering. For example: Does the wound require assessment and an updated dressing plan? Is there a pressure injury risk that requires a prevention plan and support worker training? Does the participant need a continence assessment and report to support a review of consumables or support needs?
A good referral does not need to diagnose the issue. It needs to identify why clinical input is required and why ordinary support arrangements may not be enough.
How to prepare nursing referrals with useful clinical detail
The most helpful referrals give a short, factual picture of the participant’s health needs and current routine. Think of it as handing over the information a nurse would need to make safe decisions before arriving at the home.
Include the participant’s name, preferred contact method, address, NDIS details where relevant, nominated decision-maker and any communication needs. Confirm that the participant or guardian has consented to the referral and to relevant information being shared. Consent is particularly important where family members, providers and multiple health professionals are involved.
Then explain the clinical concern in plain language. Include when it started, whether it is worsening, how often it occurs and any recent changes. A brief timeline is valuable. For a wound, this could include the location, duration, current dressing, exudate or odour concerns, pain, infection history and whether the wound is deteriorating. For bowel and bladder care, it may include constipation, incontinence patterns, catheter blockages, skin breakdown, current products and any hospital presentations.
It is also useful to identify what is currently working. If a participant prefers a particular approach to personal care, has a reliable routine or communicates pain in a specific way, that information supports safe, dignity-focused care from the first visit.
Describe risk, not just tasks
Referrals are stronger when they explain the consequence of leaving the issue unresolved. This is not about overstating need. It is about making genuine clinical risk visible.
For example, repeated moisture-associated skin damage may increase the risk of pressure injury and infection. Inconsistent insulin administration may create a risk of hypoglycaemia or hyperglycaemia. A stoma appliance that is frequently leaking can lead to skin injury, distress and reduced confidence leaving home. Support workers who have not been trained in a high-intensity task may be unable to provide care safely or consistently.
Where known, document recent emergency department presentations, hospital admissions, ambulance call-outs, GP reviews or infection treatment connected to the concern. These details help a nurse understand urgency and can provide useful context for future nursing reports. They should be factual, dated where possible and relevant to the referral reason.
Include the current care arrangements
A nurse needs to understand who is providing care and where uncertainty sits. Note whether care is delivered by family, support workers, a SIL provider, district nursing, a GP or other clinicians. Include the frequency of supports and whether there are gaps on particular days or times.
State whether current staff have received training and whether a clinical care plan exists. If one does, provide the latest version and identify whether it remains suitable. Care plans can become outdated after a hospital admission, change in mobility, new medication, weight loss, increased incontinence or a decline in skin integrity.
This context helps determine whether the referral needs an assessment only, a detailed clinical care plan, support worker training and clinical oversight, ongoing nursing visits, or a combination of these. The right response depends on the participant’s presentation and risks. A stable routine may require an updated plan and competency-based training, while an unstable wound or escalating catheter issue may require more frequent nursing review.
Attach evidence that informs the assessment
Relevant documentation can prevent duplicate assessments and make the first appointment more productive. Attach only records needed for the clinical issue, and only with appropriate consent.
Useful information may include recent hospital discharge summaries, GP letters, medication charts, pathology or specialist recommendations, existing wound charts, continence product details, diabetic management plans and current clinical care plans. For skin or wound concerns, dated photographs can be helpful when they have been taken and shared in line with consent and privacy requirements. Images should never replace a clinical assessment, especially when infection, rapid deterioration or severe pain is present.
For NDIS-related referrals, include the current plan dates and identify whether the participant is approaching a plan review or has experienced a change of circumstances. Explain what evidence is needed. A nursing report may need to describe functional impact, clinical risks, recommended supports, consumable needs, staff training requirements or the consequences of inadequate clinical oversight.
Clear reports for Support Coordinators are most useful when the referral identifies the decision that needs supporting. A general request for “a report” is less effective than a request that explains the participant’s change in needs and the purpose of the evidence.
Be clear about urgency and escalation
Not every referral can wait for a routine assessment. Say if the issue is urgent and explain why. Examples include a wound showing signs of infection, a new or worsening pressure area, repeated catheter blockages, inability to manage a stoma, unexplained blood in urine or stool, significant changes in blood glucose management, or medication concerns that may place the participant at risk.
A referral is not a substitute for urgent medical care. If the participant is acutely unwell, has severe symptoms or there is an immediate risk to life, contact emergency services on 000. For concerns requiring prompt medical review but not an emergency response, follow the participant’s GP, treating team or local health service escalation pathway.
Giving this information upfront allows the nursing service to triage appropriately and prevents a clinically urgent concern being treated as a standard paperwork request.
Set practical goals for the first nursing input
The best referrals name the outcome needed, while leaving room for the nurse’s assessment. Goals may include establishing a safe bowel or bladder routine, reducing wound deterioration, preventing pressure injuries, reviewing skin integrity, improving medication safety, assessing continence needs, developing a clinical care plan or training support workers in a specific high-intensity support.
Keep goals grounded in the participant’s circumstances. A participant may need a care plan that makes daily routines safer and less distressing for everyone involved. A family may need clinical guidance after a hospital discharge. A Support Coordinator may need defensible nursing evidence to explain why existing supports no longer match the person’s health needs.
This is where practical nursing assessments add value. They connect clinical findings with what must happen in the home: who does what, when to escalate, what supplies are required, how dignity will be protected and how staff competency will be maintained.
Avoid the common referral gaps
The most common delay is a referral with no clear contact person, no consent confirmation or no explanation of the current clinical concern. Another is relying on broad labels such as “complex participant” without describing the actual health risks and care tasks.
Avoid sending outdated documents without noting that circumstances have changed. Do not assume a previous hospital discharge plan remains appropriate in a community setting. It may require adaptation, training and ongoing clinical oversight before it can be implemented safely by support workers.
Finally, do not wait for a crisis before seeking nursing input. Early referral for recurrent skin problems, continence changes, pressure areas or uncertainty around complex procedures can reduce avoidable escalation and help participants stay safe at home.
For Adelaide participants with complex health support needs, Compassion Wings provides nurse-led NDIS care focused on assessment, practical care planning, clinical reporting and support worker education. A well-prepared referral gives the nursing team a strong starting point, but the purpose remains simple: safe care that respects the participant, supports the people around them and responds before manageable risks become emergencies.