








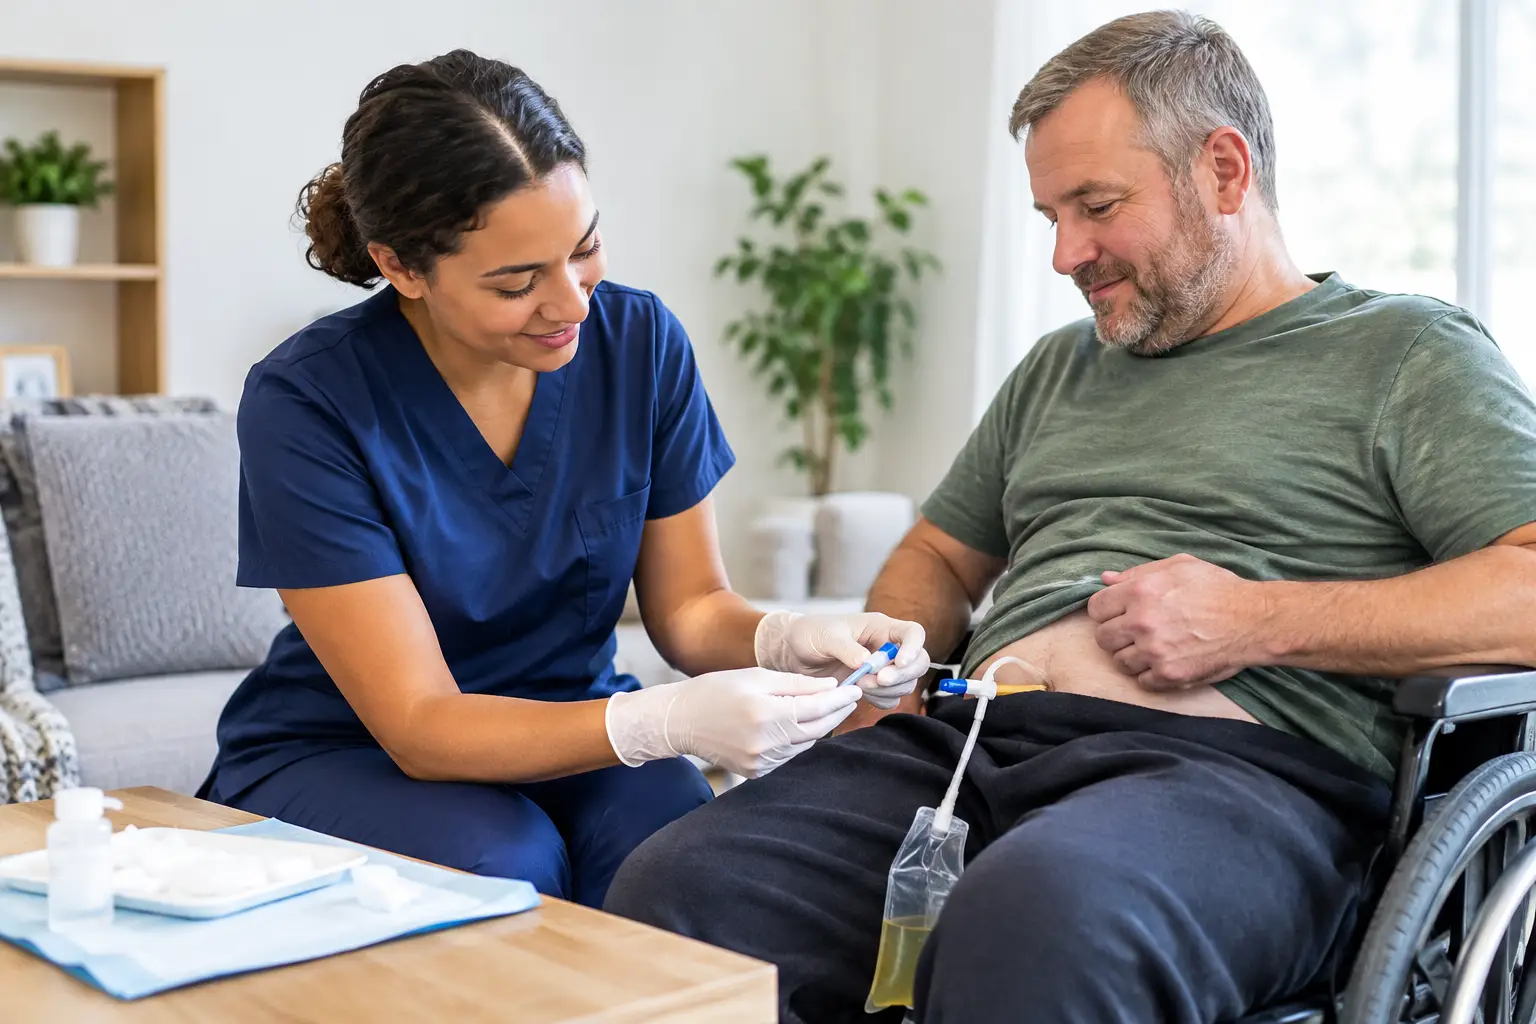
Best Steps for Catheter Routines at Home
A catheter routine can look straightforward on a care plan, yet small gaps in hygiene, drainage positioning or observation can quickly lead to pain, skin damage, blockages or infection. The best steps for catheter routines are therefore not simply a checklist. They are an individualised, nurse-led approach that protects comfort, dignity and clinical safety every day.
For NDIS participants with an indwelling urethral catheter or suprapubic catheter, the right routine needs to reflect their catheter type, medical history, hand function, mobility, cognition, bowel pattern, skin integrity and support environment. A routine that works well for one person may be unsafe or impractical for another.
Best steps for catheter routines start with a clear care plan
A current clinical care plan gives families, support workers and providers a shared understanding of what safe catheter care looks like for that participant. It should record the catheter type and size where relevant, the drainage system used, usual urine appearance and output, known risks, prescribed fluid guidance, catheter change arrangements, and clear escalation instructions.
The plan also needs to distinguish between tasks that a participant can safely complete themselves, tasks that can be undertaken by trained support workers, and tasks requiring a nurse or medical practitioner. This matters particularly where high-intensity supports are involved. Good intentions do not replace assessed competency, current instructions and clinical oversight.
Practical nursing assessments can identify issues that are often missed in a busy household or support setting. For example, recurrent pulling on the catheter may be related to poor tubing placement, a fixation issue, transfer technique, discomfort, confusion, constipation or an unsuitable drainage setup. A nurse can assess the cause rather than treating each episode as an isolated incident.
Build hygiene into the routine, without overcomplicating it
Hand hygiene should happen before and after handling the catheter, tubing, bag or drainage tap. The catheter entry site and surrounding skin should be cleaned as directed in the person’s care plan, usually as part of normal daily hygiene. Avoid applying creams, powders or antiseptics around the site unless they have been specifically recommended by the treating team.
For a urethral catheter, gentle cleaning around the catheter where it enters the body is essential. For a suprapubic catheter, the stoma and surrounding skin need regular observation for redness, discharge, overgrowth of tissue, moisture damage or pain. The aim is safe, dignity-focused care, not aggressive cleaning that irritates vulnerable skin.
A closed drainage system should remain closed unless there is a clinical reason to disconnect it. Unnecessary breaks in the system can increase infection risk. If a bag change, valve routine or specimen collection is required, the care plan should state who is responsible and the exact procedure to follow.
Keep drainage flowing freely
Most day-to-day catheter problems are practical problems first. Tubing can become trapped under a leg, caught on a wheelchair, kinked during a transfer or pulled tight when a person turns in bed. Each support shift should include a quick visual check that tubing is not twisted, compressed or under tension.
The drainage bag should stay below bladder level so urine can drain by gravity, but it must never rest on the floor. Securement devices can reduce traction and discomfort, provided they are applied in the correct position and reviewed if the person’s body shape, mobility or clothing changes.
Empty the drainage bag according to the person’s routine and before it becomes overly full. This reduces weight and pulling on the catheter, makes output easier to observe, and lowers the risk of spills. Use a clean container where required, avoid allowing the tap to touch surfaces, and document concerns rather than relying on memory at handover.
Fluid advice must be individualised. Many people benefit from appropriate fluid intake, but some have fluid restrictions due to cardiac, renal or other health conditions. Support workers should never encourage extra fluids without checking the current clinical plan or medical advice.
Observe the person, not only the bag
Urine colour and volume are useful indicators, but they never tell the whole story. A person may be developing a catheter-related issue even when the bag appears to be draining. Changes in pain, behaviour, appetite, alertness, continence around the catheter, lower abdominal discomfort, spasms or new agitation can all need attention.
Some sediment, odour or changes in colour may occur for reasons that are not urgent. However, a pattern of change, particularly alongside symptoms, should be documented and escalated. Catheter-associated urinary tract infections can present differently in people with complex disability, communication differences or cognitive impairment. Staff who know the participant’s usual presentation are often best placed to notice subtle change early.
A bowel routine also matters. Constipation can contribute to discomfort, bladder spasms, leakage around the catheter and reduced drainage. Catheter care should therefore sit alongside the participant’s broader bowel and bladder care plan, not operate as a separate task.
Know when to escalate without delay
A clear escalation pathway prevents uncertainty during a support shift. Support workers and families should know who to call first, what information to provide, and when urgent medical assessment is required. The response will depend on the participant’s health history and clinical instructions, but prompt nursing or medical advice is generally needed if there is:
- no urine draining with symptoms of discomfort, bladder fullness or distress
- a catheter that has fallen out, been pulled out, or is visibly damaged
- new heavy bleeding, large blood clots, severe pain or significant leakage
- fever, rigors, confusion, marked drowsiness, vomiting or signs of becoming acutely unwell.
Do not attempt to reinsert, flush, inflate or alter a catheter unless this is within the person’s prescribed plan and the worker has been specifically trained and assessed as competent. Improvised responses can cause trauma, delay appropriate treatment or obscure the clinical picture.
When seeking advice, record the time the problem was noticed, symptoms, urine appearance and approximate output, any recent bowel action, fluid intake where relevant, catheter traction or dislodgement, and actions already taken. This information helps the nurse or treating clinician make safer decisions quickly.
Documentation makes routine care safer
Clinical documentation is not paperwork for its own sake. It creates continuity when several support workers, family members and health professionals are involved. A brief, factual record can show whether a concern is new, whether it is recurring, and whether earlier interventions have worked.
Shift notes should capture observations that differ from the participant’s baseline, care completed, bag changes or emptying where required by the plan, skin concerns, leakage, pain, escalation contacts and outcomes. Entries should be objective. Instead of writing “urine looked bad”, record the observable change and associated symptoms, such as darker urine, cloudiness, odour, reduced output or reported burning.
For Support Coordinators, accurate records and nursing reports can provide useful evidence when a participant’s needs have changed. Recurrent blockages, skin breakdown, infection risk, increased dependence, catheter-related hospital presentations or the need for additional training may indicate that the existing supports and clinical plan require review. Clear reports for Support Coordinators help connect daily risks with the practical supports needed to manage them safely.
Training turns a plan into reliable care
A well-written care plan is only effective when the people implementing it understand it. Support worker training and clinical oversight should cover the participant’s specific catheter system, infection prevention, bag positioning, securement, skin observation, documentation and escalation pathway. It should also address privacy and respectful communication.
Training should not be treated as a one-off induction. Staff turnover, changing health needs, a hospital admission or repeated incidents are all reasons to revisit competency. Refresher education is particularly valuable when workers are unsure how to distinguish a manageable routine issue from a clinical concern.
For participants and families, this approach can reduce the pressure of having to repeatedly explain complex care needs to new staff. For providers and Support Coordinators, it creates a more consistent, audit-ready approach to high-intensity clinical support in the home.
When a nursing review is needed
A nursing review is sensible when catheter issues are frequent, the routine is unclear, support workers have inconsistent practices, the participant has new leakage or skin problems, or there has been an emergency department presentation or hospital discharge. It is also useful before a new provider commences supports, so risks are assessed rather than assumed.
Compassion Wings provides nurse-led NDIS care across Adelaide, including catheter-related assessment, clinical care plans, support worker education and nursing reporting. The focus is practical: identifying risks early, setting out actions clearly and helping participants stay safe at home.
The most reliable catheter routine is one that fits the person, is understood by everyone involved and is reviewed before minor problems become major ones. When observations change or the routine no longer feels safe, asking for clinical input early is a protective step, not a failure of care.





