








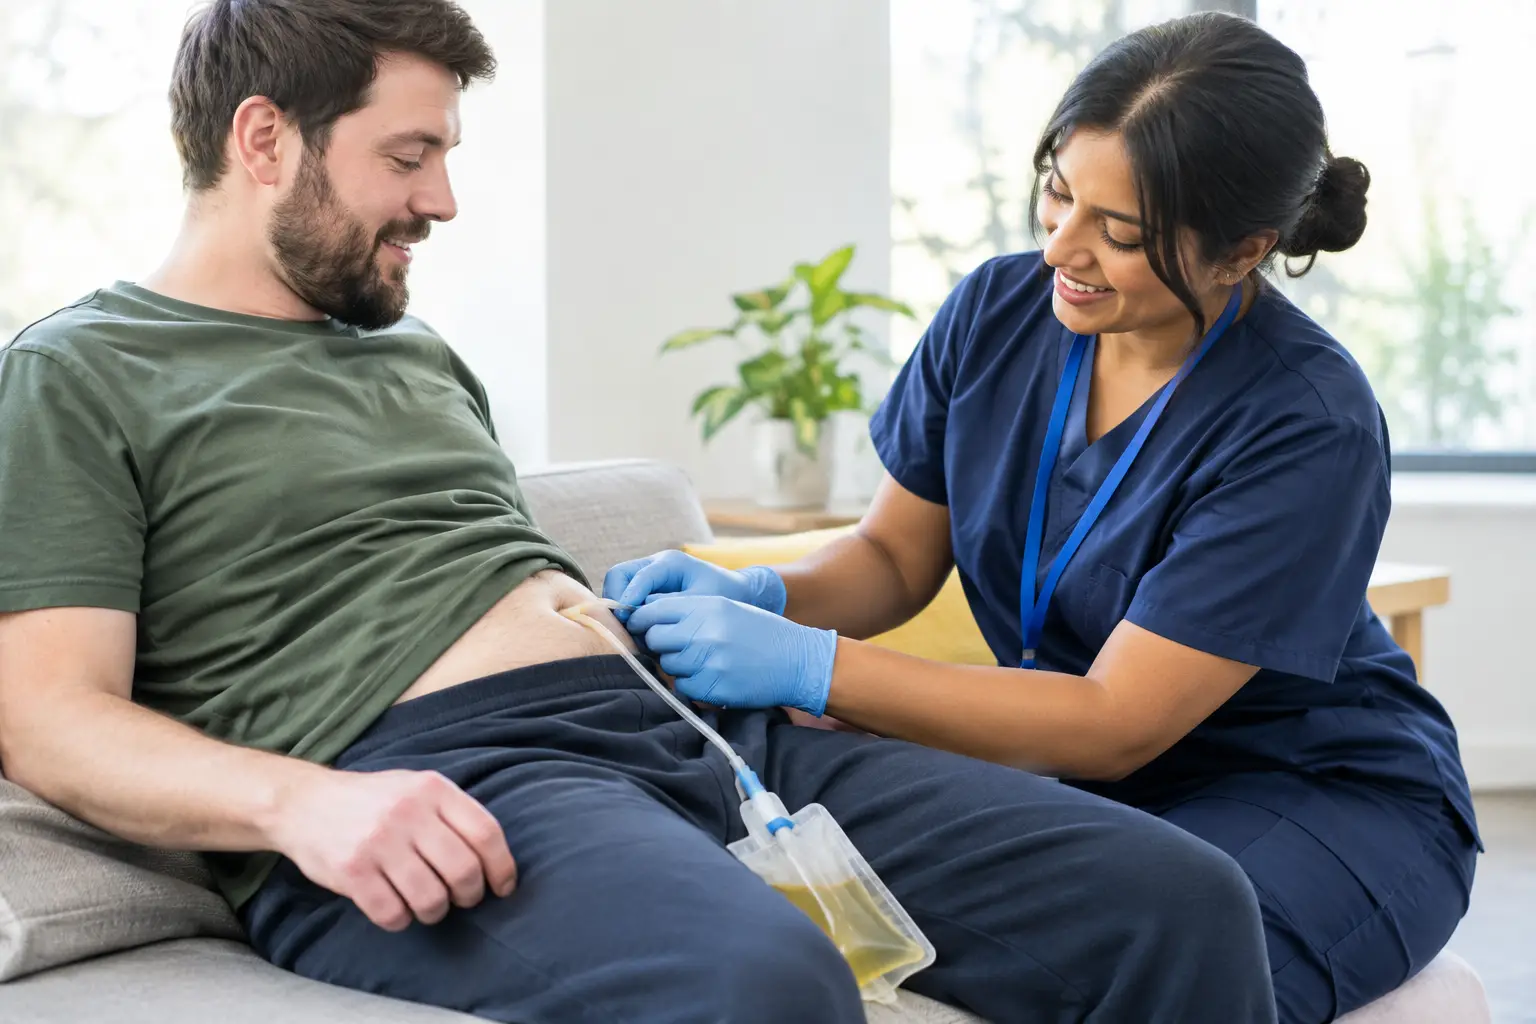
Is Catheter Care High Intensity for NDIS Teams?
A drainage bag that is not emptying, new lower abdominal pain, leaking around a catheter or a sudden change in urine colour can become a clinical issue quickly. That is why the question, is catheter care high intensity, matters to participants, families, support providers and Support Coordinators. The answer is not always a simple yes. It depends on the catheter type, the task being performed, the participant’s health risks and the level of clinical oversight in place.
For NDIS participants with complex bladder care needs, a nurse-led assessment turns uncertainty into a practical plan. It identifies what can be safely completed by the participant or a trained support worker, what requires a nurse, and exactly when staff must escalate.
Is catheter care high intensity under the NDIS?
Catheter-related support can fall within high-intensity daily personal activities when it involves complex health risks, specialised knowledge, worker competency requirements or close clinical oversight. However, having a catheter does not automatically mean every related task is high intensity.
For example, an established, stable routine for emptying a drainage bag may be undertaken by a properly trained worker when there is a clear care plan and the participant’s needs are predictable. The risk profile changes where there is a suprapubic catheter, recurring blockages, frequent urinary tract infections, autonomic dysreflexia risk, impaired communication, difficult anatomy, recent catheter changes or a history of hospital presentations.
The key question is not simply, “Does this person have a catheter?” It is, “What task is required, what could go wrong, and does the worker have the documented training, directions and support to respond safely?”
A practical nursing assessment considers the full clinical picture rather than applying a label to the diagnosis alone. This is particularly valuable for Support Coordinators who need clear reports for Support Coordinators, provider teams and plan review evidence.
The catheter tasks that need different levels of support
Catheter care covers a broad range of activities. Each has different risks and may need different safeguards.
Routine drainage and hygiene
Routine support may include checking that tubing is not kinked, positioning the drainage bag safely below bladder level, emptying a bag using clean technique, measuring output where clinically directed, and providing hygiene around the catheter area. Even these apparently straightforward tasks need individual instructions.
A participant with reduced sensation may not recognise discomfort from traction or a blocked catheter. Someone with cognitive impairment may accidentally disconnect tubing or pull at the device. A person with recurrent infection may need more careful monitoring of symptoms and fluid intake. Safe care is never just about completing a task – it is about recognising change early.
Intermittent catheterisation
Intermittent catheterisation can require more detailed assessment, particularly where the participant cannot perform the procedure themselves. The routine may involve sterile or clean technique as prescribed, timing requirements, privacy considerations, infection prevention and a clear response to resistance, bleeding or failure to drain.
This is not an activity to leave to assumption or verbal handover. Workers need role-specific training and assessed competency, while the care plan needs to state the approved procedure, required equipment, usual pattern and escalation pathway.
Indwelling and suprapubic catheters
Indwelling urethral and suprapubic catheters can create risks such as blockage, bypassing or leakage, skin irritation, accidental removal, infection and trauma. A suprapubic site also requires monitoring for redness, discharge, pain and skin breakdown.
Catheter insertion, replacement and clinical troubleshooting are nursing or medical matters unless an appropriately qualified clinician directs otherwise. Support workers should not be expected to work beyond their training or the agreed clinical plan. Clear boundaries protect the participant and the staff member.
When nursing input is needed
Nursing input is especially important when catheter care is new, unstable or linked to another complex condition. A referral is appropriate after hospital discharge, a new catheter insertion, a transition between providers, repeated urinary tract infections, unexplained leaking, skin concerns or changes in a participant’s ability to manage their own routine.
It is also appropriate when a provider has workers supporting catheter tasks without a current care plan or documented competency process. In these situations, the risk is not only the catheter itself. Inconsistent practice, unclear escalation and gaps in documentation can delay care when something changes.
A nurse-led NDIS care assessment can establish the baseline: catheter type and size where relevant, reason for use, usual output, bag-change routine, skin condition, prescribed supplies, known complications, treating team contacts and individual warning signs. It should also account for dignity, consent, communication preferences and how the participant wants support delivered in their home.
What a safe catheter care plan should include
A useful clinical care plan is practical enough for workers to follow during a busy shift, while still giving coordinators confidence that risks have been considered. It should be written in clear language and reviewed when needs change.
For catheter support, the plan should set out the participant’s normal routine, the tasks each worker role may perform, infection-control requirements, equipment and storage needs, documentation expectations and escalation contacts. It must also identify the signs that require prompt clinical advice or urgent medical assessment.
Examples can include no urine draining when the participant is uncomfortable or has bladder fullness, a catheter that has fallen out, heavy bleeding, new severe pain, fever or chills, increasing confusion, significant leakage, a damaged catheter system, or symptoms specific to the person’s known risks. For participants at risk of autonomic dysreflexia, the plan needs explicit urgent-response directions agreed with the treating team.
A generic template is rarely enough. One participant may safely use a leg bag throughout the day and a night bag overnight, while another requires output monitoring because of renal concerns or fluid restrictions. Practical nursing assessments make these distinctions visible.
Training is more than a one-off demonstration
Support worker training and clinical oversight are central to safe catheter-related support. Watching a procedure once does not demonstrate that a worker can complete it safely, maintain privacy, identify complications or document a concern correctly.
Training should be specific to the participant’s catheter routine and the tasks the worker is expected to undertake. It should cover hand hygiene, equipment handling, positioning, preventing traction, observing output and skin condition, safe disposal, documentation and escalation. Competency should be assessed and recorded, then refreshed when routines change or a clinical incident occurs.
This approach also supports provider governance. It gives service managers a defensible record of what workers have been trained to do, and it avoids placing staff in situations where they feel pressured to make clinical decisions beyond their role.
Documentation that supports safe NDIS decisions
For Support Coordinators and Plan Managers, catheter needs can be difficult to explain if the information is scattered across discharge summaries, shift notes and family reports. A nursing report can bring the evidence together in a clear, functional way.
Good documentation describes the support required, why it is required, the risks without appropriate care, the frequency of clinical review, training needs and the consequences of gaps in support. It should connect clinical findings to the participant’s day-to-day safety at home without making unsupported claims about funding.
Where catheter care has become more complex, a current nursing assessment may also assist with a plan review or change of circumstances. The strongest evidence is specific: recurring blockage events, infection history, altered function, new care requirements, worker competency needs and the clinical rationale for oversight.
A practical next step for Adelaide referrals
If a participant’s catheter routine is unclear, has changed, or relies on workers who have not received individualised training, start with a clinical assessment rather than trying to solve the issue through informal instructions. Bring together the current discharge information, medication list where relevant, catheter supplies, recent incidents and details of the support roster.
Compassion Wings provides clinical support in the home across Adelaide, including practical catheter assessments, individualised care plans, support worker training and nursing reports. The focus is safe, dignity-focused care that helps participants stay safe at home while giving their care team clear clinical direction.
Catheter support works best when everyone knows the routine, the limits of their role and the first signs that something is not right. That clarity gives participants more privacy and confidence, and it gives families and coordinators a safer path forward.




